

Seeking Alternatives to Hard End Points
Is Imaging the Best APPROACH?
.
Atheroma burden is a strong predictor of future events, especially in diabetic individuals,6 and, not surprisingly, imaging the morphology of the vessel wall with IVUS has been a fruitful area of research. From using IVUS to understand the morphology in atherosclerosis in diabetic individuals, it has been used in the current study as a possible surrogate for future events and a predictor of efficacy of therapy. Although used in multiple studies, this approach raises important questions for investigative strategies. Is the change in plaque volume a good surrogate for future events (the main parameter that the physician and the patient are concerned with), or should we image more than just plaque volume to understand this risk? It is important to recognize that the surrogate primary end points, such as PAV, offer potential in terms of evaluating the progression or regression of atherosclerotic process, and allow for rather smaller clinical trials in comparison with those powered for clinical events. However, convincing evidence that links PAV to change in cardiovascular risk is still lacking, and this makes IVUS-based trials, even if the results are strongly positive, still not entirely conclusive. One could argue that nearly 10 years’ worth of multiple IVUS-based studies have provided important incremental information that, however, has not yet been translated into a robust clinical event or outcome-related correlation. It might thus be time to move on to explore techniques that go beyond IVUS-verified PAV and to establish the relationship between IVUS characteristics and outcomes.
.
Editorial discute o estudo “Efeito da rosiglitazona na progressão da aterosclerose coronária em pacientes com Diabetes Mellitus Tipo 2 e Doença Arterial Coronariana”
APPROACH.
.
Não houve regressão ou diminuição da progressão significativa da Aterosclerose ao Ultrassom coronário com o uso de uma glitazona.
.
Sempre que uma droga falha em reduzir a Aterosclerose, questionam se o exame é eficiente para isso.
Deveriam questionar se a droga é realmente boa para esse destino.
.
Clinicamente, as glitazonas estão na zona “zinza” do benefício para coronariopatia.
Isso não é culpa do ultrassom.
.
Quando o caçador é míope, põe a culpa no cão!
.
Mês: março 2010
BAVT ao Ecocardiograma
.
.
Só por curiosidade…
Veja a onda E ou e´sem a onda A a seguir, em várias formas.
.
PCR só vale para quem tem Aterosclerose

Association of Carotid Artery Intima-Media Thickness, Plaques, and C-Reactive Protein With Future Cardiovascular Disease and All-Cause Mortality
.
Conclusions— In older adults, elevated CRP was associated with increased risk for CVD and all-cause mortality only in those with detectable atherosclerosis based on carotid ultrasound.
Circulation. 2007;116:32-38
.
Nesse estudo, acima de 65 anos, a PCR só foi marcadora de risco em pacientes que já apresentavam Aterosclerose carotídea acelerada.
.
Podemos pensar que a inflamação de início recente não consegue acelerar a doença vascular e iniciar eventos clínicos?
.
De qualquer forma, mais um estudo a demonstrar o papel da IMT na análise do paciente.
Sem radiação, sem contraste, com baixo custo.
.
Espessura da Carótida e o risco futuro.
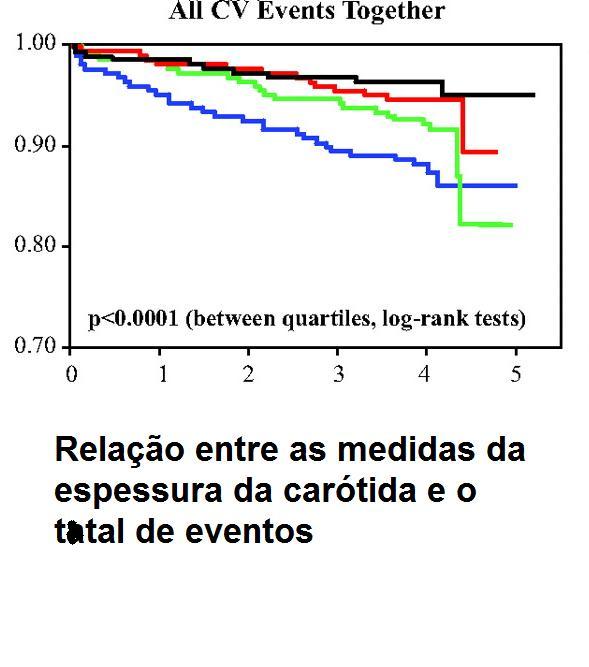
Conclusions— ELSA shows that carotid intima-media thickening and plaques are important added risks of cardiovascular outcomes in a treated hypertensive population independently of blood pressure and traditional risk factors. However, the analysis failed to show a predictive role of treatment-dependent IMT changes. These negative conclusions should be tempered by the limitations inherent in the smallness of these changes compared with the large individual differences in baseline IMTs.
.
Estudo mostra a espessura da carótida como bom marcador de risco (Circulation. 2009;120:1084-1090) mas sem evidências do efeito do tratamento na espessura e repercussão clínica.
.
Alguns colegas não entendem a importância do IMT.
É difícil mesmo, caso acredite na doença arterial por conceitos antigos.
Nosso corpo não se divide em compartimentos independentes.
A saúde ou doença é sempre difusa.
Onde existirem artérias, teremos Aterosclerose.
.
Como medimos a pressão e ficamos satisfeitos em tratarmos o marcador chamado pressão arterial aferida no braço?
Foram necessários décadas para provar que tratar a pressão aferida valia a pena.
Tempo que a IMT ainda não teve.
.
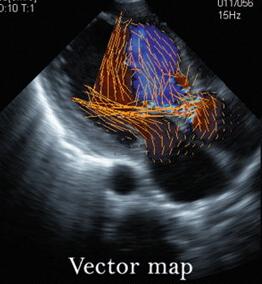
Mapeamento dos vetores de fluxo, novo método.
Aqui
Quantification of chronic aortic regurgitation by vector flow mapping: a novel echocardiographic method
.
Conclusion RegR measured by VFM, a new Doppler method allowing quantitative analysis of FV in spite of the presence of turbulent flow, is a highly reproducible parameter with good accuracy for AR quantification.
.
O ecocardiograma tem se limitado a estudar o fluxo apenas por suas velocidades.
Agora é possível estudar os vetores de cada fluxo ou refluxo.
.
Dá até para estimar melhor a regurgitação aórtica.
Acredito ser um método promissor. Veremos se funciona bem na insuficiência Mitral, outro grande desafio.
.
Mais uma para o transesofágico.

Transthoracic second harmonic two- and three-dimensional echocardiography for detection of patent foramen ovale
.
Conclusion In this cohort of patients, TEE confirms the role of ‘gold standard’ exam for the detection of PFO; the non-invasive methods, and the TTE in particular, present a good diagnostic accuracy, but are inferior to the TEE because of the low negative predictive value and the non-optimal detection of small shunts. If the only purpose of TEE is the detection of significative interatrial shunt, TEE can be replaced by TTE. The R3DTE presents a good diagnostic accuracy, provides a better anatomical definition of the interatrial septum, and may have a role in this setting of patients, but does not add a lot to the TTE for the diagnosis.
.
A leitora de Portugal, Ana, sugeriu o artigo acima, que é muito bom.
.
Mostra como o 3D transtorácico não supera o exame semi-invasivo transesofágico.
Para quem aprecia imagens de alta definição, o transesofágico dá um show. Sendo 3d ainda, espetáculo de imagens.
.
Parece que o uso do transesofágico está garantido, por enquanto.
Só falta um preço mais decente.
.
Enfim, somos ouro! 3D Transesofágico

.
A sociedade européia de ecocardiografia definiu o ecocardiograma transesofágico 3D como o método ouro na avaliação de valvopatias.
.
Ou seja, os outros métodos serão corrigidos por ele!
Na dúvida, a palavra final é do 3D TEE.
.
Definitivamente, vou jogar fora minha bola de cristal, previ que o TEE iria desaparecer…
.
Cateterismo sem isquemia comprovada

O cateterismo cardíaco é solicitado na suspeita de coronariopatia significativa.
.
Em Campinas a porcentagem foi de 32% normais e 12% com redução leve/moderada numa amostra de 1900 cateterismos.
.
Pelo menos 1/3 poderiam ter sido evitados, ou seja, 627.
.
O custo total dos normais é aproximadamente 1.800.000,00, quase 2 milhões.
.
Caso fizessem ecostress pela UNIMED, gastariam 160 mil reais.
Com a sensibilidade de 90% para doença significativa, só 63 cateterismos normais seriam obtidos.
.
Daria para economizar uns 1.500.000,00 reais, no mínimo.
.
E tem gente que acha que fazemos ecostress demais em Campinas…
.
E só estou usando regras de diretrizes, sem pensar no entendimento mais recente da fisiopatologia da doença coronária.
.
Mas as batatas vão para os diretores, digo, vencedores!
.
Europa: Recomendações para endocardite
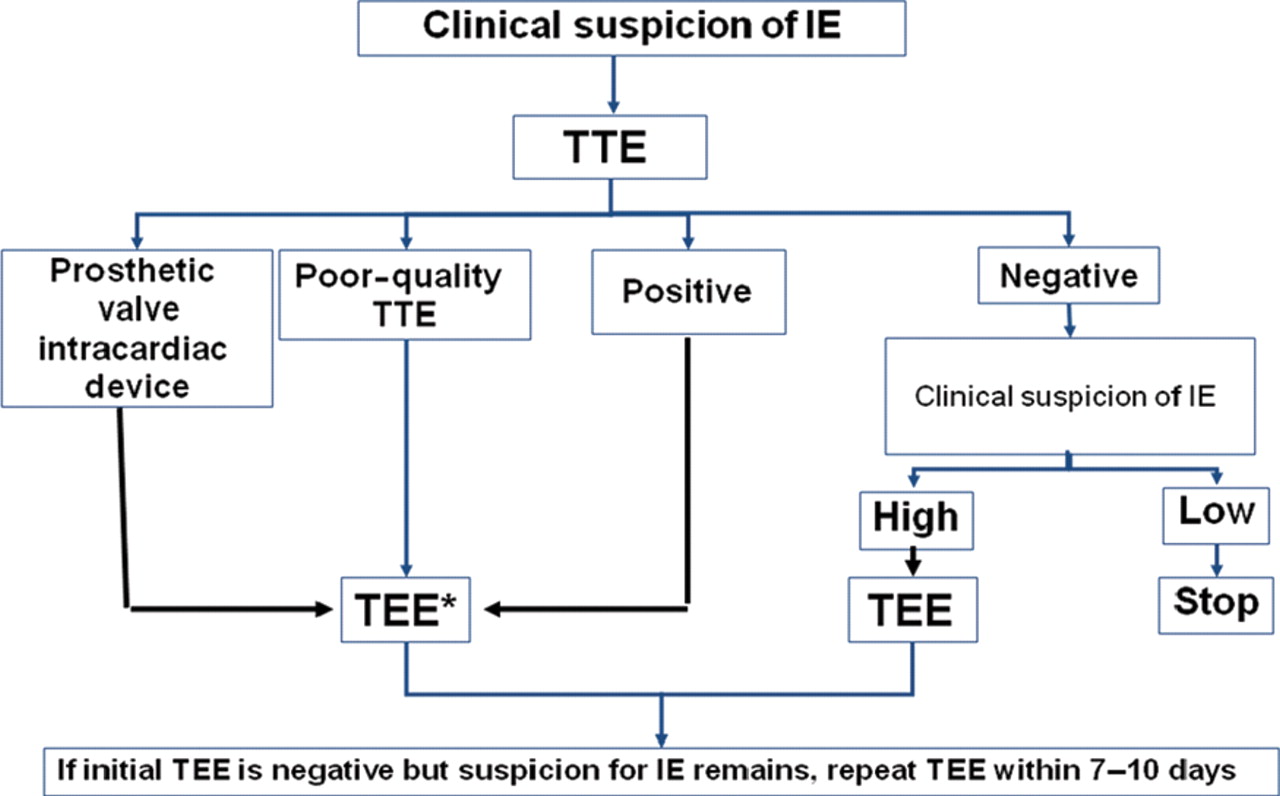
Recommendations for the practice of echocardiography in infective endocarditis FREE
.
Recommendations
TTE is recommended as the first-line imaging modality in suspected IE;
TEE is recommended in patients with high clinical suspicion of IE and a normal TTE;
TEE should be considered in the majority of adult patients with suspected IE, even in cases with positive TTE;
Repeat TTE/TEE within 7–10 days is recommended in case of initially negative examination when clinical suspicion of IE remains high;
TEE is not indicated in patients with a good-quality negative TTE and low clinical suspicion of IE.
.
A sociedade européia recomenda fazer o transesofágico mesmo em quem já tem um transtorácico positivo para endocardite!!!
.
Então vamos fazer.
.